Generalized Pustular Psoriasis: Review Maps Current and Emerging Therapies
Updated
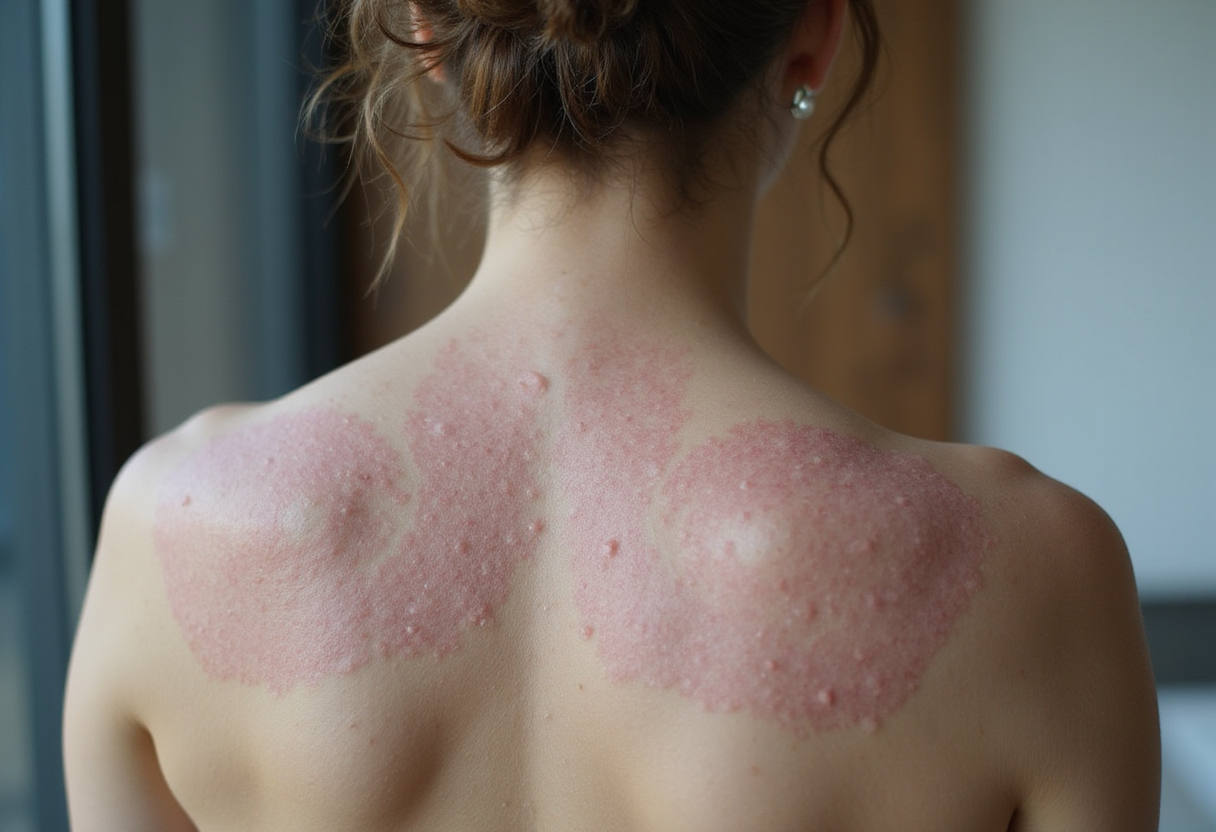
Generalized pustular psoriasis (GPP) remains one of the most challenging presentations dermatologists encounter: a rare, potentially life-threatening neutrophilic skin disease marked by widespread sterile pustules, fever and systemic inflammation, frequently flaring without the plaques that define plaque psoriasis. A new review published in Cureus consolidates the current treatment hierarchy and catalogs the innovative therapies now reshaping management of the disease.
The review arrives at a moment when GPP management is moving rapidly. For decades, clinicians relied on agents borrowed from plaque psoriasis and other inflammatory diseases — systemic retinoids, methotrexate, cyclosporine and corticosteroids — with evidence limited to case series, retrospective cohorts and expert consensus rather than randomized trials. That evidence base constrained confidence, because GPP's rarity makes prospective study difficult and because the disease's flare-and-remission course complicates interpretation of open-label data.
The pathogenic framing has shifted over the past decade. GPP is now understood as an autoinflammatory disease driven largely by the IL-36 axis, with loss-of-function mutations in the IL36RN gene identifying a distinct subset — often younger patients with more severe, recurrent flares. This mechanistic insight, alongside involvement of the IL-23/IL-17 and TNF pathways, has supplied rational drug targets and explains why therapies effective in plaque psoriasis show variable results in GPP.
The review walks through conventional systemic agents first. Acitretin remains a mainstay, consistent with its long track record in pustular disease. Cyclosporine is highlighted for rapid flare control. Methotrexate and tumor necrosis factor inhibitors retain roles in selected patients. These agents anchor treatment where access to newer biologics is limited, and the review situates them within the practical realities of GPP care: the need for swift flare suppression, attention to infection triggers — including withdrawal of systemic corticosteroids, a well-recognized precipitant — and management of systemic complications such as hypoalbuminemia and sepsis risk during severe flares.
The more consequential contribution is the survey of innovative therapies. The IL-36 receptor antagonist spesolimab now carries approval for GPP flare treatment, following randomized evidence of rapid pustule and inflammation clearance, and the review places it as a paradigm-shifting option for acute flares. Additional biologics are examined across the TNF, IL-17, IL-23 and IL-12/23 inhibitor classes, with the authors weighing published case-level and cohort evidence for each in GPP specifically rather than extrapolating from plaque psoriasis data.
This distinction matters clinically. GPP and plaque psoriasis share the psoriasis label but differ in immunology, genetics and flare behavior, and the review's structure reflects that: it evaluates drugs by their documented performance in pustular disease, not by their plaque-psoriasis indications. For drugs without dedicated GPP trials, the authors characterize the evidence class explicitly, giving readers a transparent view of where randomized data exist and where clinical experience still drives choices.
For practicing dermatologists, the review functions as a treatment map rather than a guideline. It organizes options by clinical scenario — acute flare management versus maintenance of remission — and emphasizes that the goals differ: rapid resolution of pustulation and systemic symptoms during flares, prevention of recurrence between them. That framing aligns with how regulators now evaluate GPP therapies, with flare resolution and time-to-flare emerging as the endpoints that matter most to patients.
Access and sequencing questions remain open. Biologic availability varies by country, cost remains a barrier in many systems, and head-to-head comparisons across mechanisms are absent from the literature. The review acknowledges these gaps and identifies them as priorities for future research, alongside longer-term safety data for newer agents and better characterization of genotype-phenotype relationships that could guide individualized drug selection.
The trajectory the paper documents is clear: GPP has moved from a disease managed almost entirely by inference to one with targeted, trial-supported therapy. As IL-36-axis science matures and additional agents advance through development, dermatologists can expect a progressively more evidence-based algorithm — one the authors argue should be refined through international registries and collaborative trials capable of enrolling this rare population at scale.
Source: Google News: Psoriasis treatment
Tom Whitfield
Show full bio
Senior reporter covering companies, deals and strategy in Clinical dermatology, inflammatory skin disease and biologics at Derm Field.