GLP-1 Receptor Agonist Added to Biologic Therapy Improved Quality of Life in Psoriatic Disease
Updated
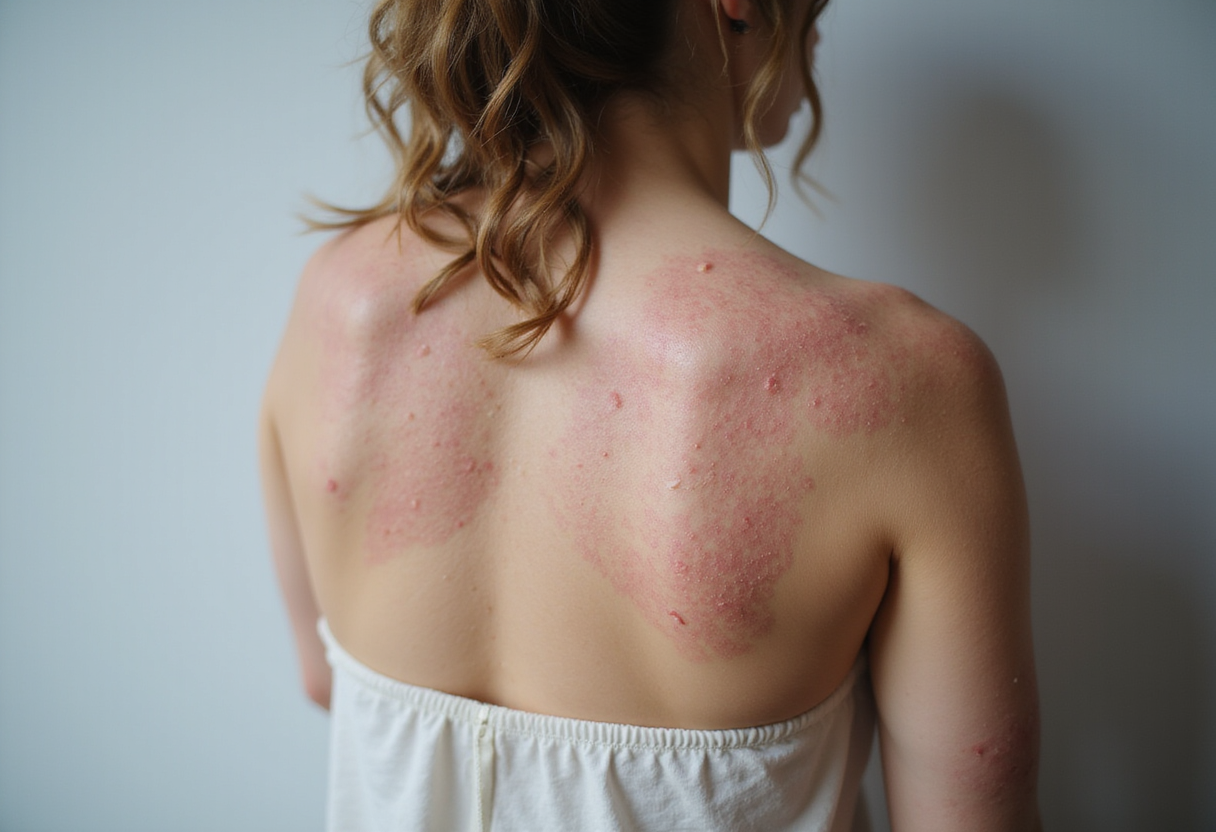
Adding a GLP-1 receptor agonist to biologic therapy improved quality of life in patients with psoriatic disease, according to a report published by Medscape.
The finding speaks to a question that has moved rapidly from the margins of dermatology toward its center: what role should metabolic therapy play in the management of psoriasis and psoriatic arthritis? GLP-1 receptor agonists — the drug class behind semaglutide, tirzepatide-related incretin agents, and their counterparts — are already reshaping obesity medicine, type 2 diabetes care, and, increasingly, conversations in the dermatology clinic.
Psoriatic disease is the term clinicians now prefer when they want to capture the full spectrum of the condition: cutaneous plaques measured by PASI, joint involvement assessed with instruments such as DAPSA or the CASPAR criteria, and the systemic, cardiometabolic comorbidity burden that travels with both. Patients with psoriasis carry a well-documented excess risk of obesity, insulin resistance, metabolic syndrome, and cardiovascular disease. That overlap is the biological rationale for studying whether agents that improve metabolic parameters can also move dermatologic and quality-of-life endpoints.
The Medscape report centers on the combination approach: a GLP-1 receptor agonist used alongside a biologic, rather than as a stand-alone intervention. This distinction matters for practicing dermatologists. Biologic therapy — whether an IL-17 inhibitor, an IL-23 inhibitor, or a TNF antagonist — remains the anchor for moderate-to-severe disease. The reported signal suggests the addition of incretin-based therapy may deliver gains that skin-clearing metrics alone do not capture, with quality of life as the endpoint that responded.
Quality-of-life measures in psoriatic disease research typically include the Dermatology Life Quality Index (DLQI), and, where axial or peripheral joint disease is in play, instruments such as HAQ or PsAID that capture pain, fatigue, and daily function. A clinically meaningful DLQI improvement is generally anchored at a reduction of 4 points or more, and PASI 75 or PASI 100 responses remain the standard bars for skin clearance in registrational trials. Readers should consult the full Medscape report for the specific instrument, cohort size, effect size, and duration of follow-up, as those parameters define how far the finding can be generalized.
For clinicians, the practical context is hard to miss. A substantial share of patients on biologics live with obesity or prediabetes, and poor metabolic health is associated with reduced treatment response in psoriasis — including attenuated PASI improvements on TNF inhibitors and other classes. If concurrent GLP-1 receptor agonism can improve both metabolic parameters and patient-reported outcomes, the dermatologist's role in initiating or coordinating that therapy becomes a live question for practice models, payer coverage, and multidisciplinary care pathways with endocrinology.
The safety and cost profile shapes that conversation. GLP-1 receptor agonists carry a known adverse-event profile dominated by gastrointestinal effects — nausea, vomiting, early satiety — and their supply and reimbursement dynamics remain variable across markets. Those practical constraints will determine how quickly a signal like this one translates into routine combination strategies rather than academic discussion.
Cardiometabolic comorbidity management is already embedded in psoriasis care guidelines through screening recommendations; the new element here is therapeutic. Whether the quality-of-life benefit reported by Medscape reflects direct anti-inflammatory activity of the GLP-1 pathway, weight loss itself, improved biologic drug exposure with reduced fat mass, or a combination of all three remains an open mechanistic question, and one that future controlled studies will need to disentangle.
Dermatologists should watch for larger prospective trials that pair PASI and DLQI outcomes with metabolic endpoints such as HbA1c and weight change, which would give the combination strategy the evidence base needed to enter treatment algorithms for psoriatic disease.
Source: Google News: Psoriasis treatment
Tom Whitfield
Show full bio
Senior reporter covering companies, deals and strategy in Clinical dermatology, inflammatory skin disease and biologics at Derm Field.